


Still from the 1966 historical drama Hawaii, which depicted Native Hawaiians’ deaths from a measles outbreak that colonial settlers brought to the islands.
viruses interact with the power structures already at play in our society so that those who are already marginalized are left even more susceptible to danger, exacerbating existing social divides. But more important, of the variables in the equation, it is social structures that are the drivers, while viruses merely amplify The Viral Underclass, p 11
Despite advances in science, social structures facilitated the two major pandemics of my lifetime—HIV/AIDS and COVID-19. Within weeks of the first reports of a pneumonia-like illness in Wuhan, China, scientists published the virus’s genome online (Jan 10 2020). On January 22, evidence of human-to-human transmission was released in a statement by the World Health Organization. This speaks to the rapid capability of modern science to identify the biological mechanism behind viruses. In contrast, it took almost two years for researchers to isolate the HIV virus (May 1983) after the CDC first reported on early cases in June 5, 1981.
Vaccine development for COVID-19 proceeded rapidly. After the publication of this virus, Dr. Fauci, director of the National Institute of Allergy and Infectious Disease, immediately directed vaccine development; this was the project that Moderna later purchased (Woodward 2020). Mass vaccination campaigns began in earnest in the US in April 2021, promising the world false hope of “herd immunity”. The critical mRNA vaccine technology used for the COVID-19 vaccine was built off of early, failed, efforts to find a vaccine for the HIV virus in the 1990s.
However, when it comes to pandemics, the best strategy is early containment. This worked very effectively with SARS in 2002-2003, when the world narrowly missed a disruptive pandemic event. However, containment requires international cooperation, radical transparency, state-of-the-art contact tracing, and effective science communication. All of this pretty much fell apart during HIV/AIDS and COVID-19.
Discrimination
A viral underclass is produced by all the isms: racism, ableism, sexism, heterosexism, cisheterosexism, nativism, anti-Semitism, and the biggest social vector of them all, capitalism. The Viral Underclass, pp 10-11
Marginalized communities were disproportionately affected by both HIV/AIDS and COVID-19. When AIDS first emerged in the early 1980s, the majority of reported cases were among gay men. Widespread homophobia, combined with silence and inaction from the federal government (President Reagan did not publicly mention AIDS until September 1985) contributed to limited funding and delayed research efforts. Early misinformation surrounding HIV falsely framed it primarily as a disease spread through homosexual sex, and the illness was initially labeled GRID (“Gay-Related Immune Deficiency”), further stigmatizing the gay community and obscuring the broader public health threat.
In the early 1980s, officials at the CDC were working with very little resources to track HIV/AIDS. Internal memos from the CDC revealed frustration among staff that lack of funding restricted their progress. As depicted in the 1993 film And the Band Played On, CDC researchers relied heavily on shoe-leather epidemiology—personal interviews, surveys, phone interviews, and case-tracking around the country, to piece together patterns and transmission routes. Scientific process such as generating statistical models on computers, developing laboratory genomic investigations, or vaccine development were punted to other labs—notably Robert Gallo affiliated the NIH and France's Pasteur Institute. Meanwhile, people of all classes and walks of life were dying from AIDS—and this finally got attention. Thousands of individuals died annually over the next 15 years from AIDS, with the American death toll over 300,000 Americans from 1981 to 1995.
During COVID-19, this mentality took a catastrophic turn. While millions suffered illness, disability, and death, public concern was often dismissed by the capitalist ruling class as “anxious” or “paranoid,” while misinformation (and xenophobic attacks against Chinese Americans, egged on by top government officials) spread widely. At the same time, so-called “essential workers,” many employed in some of the lowest-paid sectors such as food service, warehouse operations, and agriculture, were expected to keep the capitalist economy running with minimal protection, support, or benefits. In other words, according to a Boston College law review article, they were considered ‘disposable’ (Rangel-Medina 2025). Wrongful death suits and legal claims revealed that essential workers were not only not provided protection but were deliberately placed into dangerous situations. They were forbidden from wearing masks in customer service roles, packed into overcrowded working conditions, and subjected to other fraudulent misrepresentations of COVID-19 and its threat to workers.
Funding and public attention for HIV/AIDS research increased significantly following the deaths of prominent public figures and the growing recognition that the disease extended beyond marginalized communities. Actor Rock Hudson publicly disclosed his AIDS diagnosis in 1985, bringing widespread media attention to the epidemic. Similarly, Elizabeth Glaser, spouse of actor, director, and writer, Paul Glaser, contracted HIV through a contaminated blood transfusion in 1981 while giving birth to her daughter, Ariel. She unknowingly transmitted the virus to Ariel.
Both Glaser and Ariel later died from AIDS-related illnesses. In response to her own diagnoses and daughter’s death, Glaser founded the Elizabeth Glaser Pediatric AIDS Foundation in 1988 to raise awareness and funding for pediatric HIV/AIDS research. As the epidemic increasingly affected wealthy, famous, and socially prominent individuals, broader public concern grew, leading to greater investment in research, treatment, and prevention efforts. Still, deaths from AIDS in sub-Saharan Africa peaked around 2005–2006, a decade after reliable HIV treatment had been widely established Western countries, with estimated annual deaths exceeding 1.5 to 2 million. HIV/AIDS treatments and testing were widely unaffordable or unavailable to lower- and middle-income countries, resulting in millions of deaths.
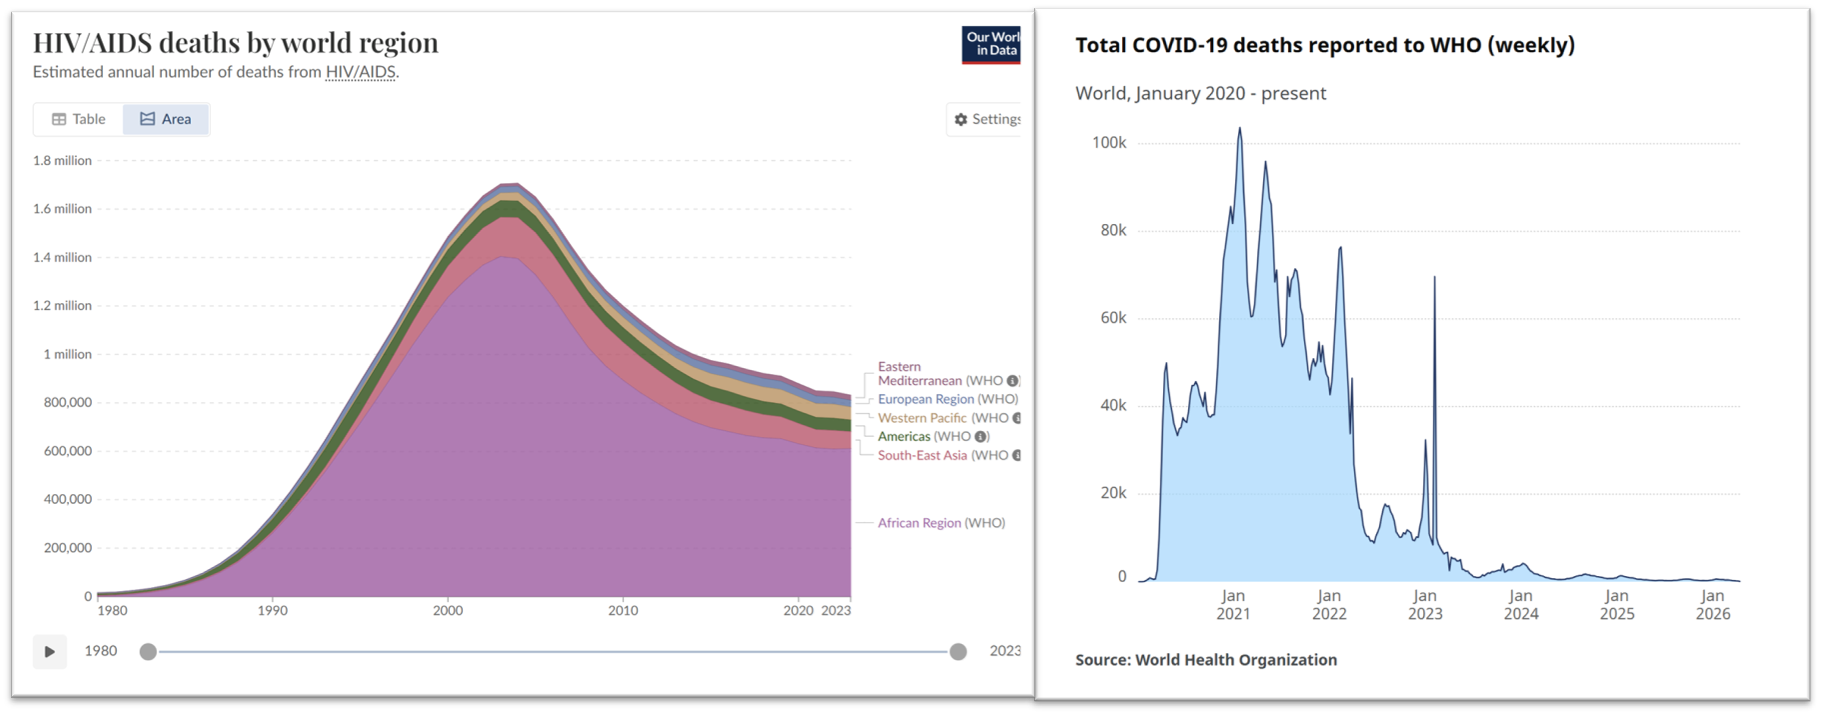
LEFT: Global Deaths from HIV/AIDS from 1980 to 2023. Deaths in the African Region peaked at over 1 million a year in the mid-2000s despite the existence of effective treatment in the Western world. RIGHT: Global deaths from COVID-19 2020-2026. Deaths peaked at over 100 thousand per week globally before effective vaccination. Overall, there have been over 7 million deaths from COVID-19 and over 44 million deaths from HIV/AIDS.
Similarly, when actor Tom Hanks publicly announced that he and his wife had contracted COVID-19 in March 2020, it helped reinforce public recognition of the seriousness and reality of the virus. Many people initially responded to warnings with denial, dismissing public concern as “panic” or exaggeration. However, the pandemic disproportionately affected those who could not afford to isolate, as well as disabled and immunocompromised individuals. The first wave of shutdowns led to tens of millions of unemployment claims and triggered the worst economic slowdown since the Great Depression.
Politics
The Risk of both of these viruses can be mitigated by simple prophylactic barriers (masks for the novel coronavirus, condoms for HIV)—both of which have spawned intense international culture wars—but also more conceptional forms of prophylaxis (like access to safe housing, stable employment, and the collection medication of populations) can protect against both. The broader idea of prophylaxis, and the elusiveness of these measures for many, reflects a commitment to care that many societies persistently resist; adopting them would mean changing the notions of inequality, manufactured scarcity, and hoarded abundance that currently organize our world The Viral Underclass, p 10
Between 1974-2010, trust in science has become more aligned with political orientation, social class, church attendance, gender, and ethnicity. Notably, conservatives have exhibited long-term declines in scientific trust over this period (Gauchat 2012). Homophobic backlash and Reagan’s alignment with the homophobic Evangelical movements surely limited funding for AIDS research.
According to reporting by Bob Woodward, the CDC was well aware of the severity of COVID-19 very on. In January 2020, George Gao, head of the Chinese CDC, was reported in telling U.S. CDC Director Robert Redfield about the spread it China— “It’s much, much worse than you’re hearing” (p. 219). By January 15, Redfield feared that the health crises would rival that of the 1918 influenza pandemic, which had killed an estimated 675,000 Americans and 50 million people worldwide. He activated the entire CDC to work on the new virus. On February 25, the Director the Center for Immunization and Respiratory Diseases at the CDC, Dr. Nancy Meissonier, finally issued a stark public warning about the possibility of school closures, and limits to in-person gathering (Woodward 2020).
There was immediate backlash by conservative commentators who jumped on this statement as a conspiracy to undermine the Trump administration. By this point, Redfield was aggressively monitoring the situation in the U.S. On February 15, 2020, Case #15 of COVID-19 was reported in Vacaville, California. Redfield, when questioned by a reporter, stated that “The American public needs to go on with their normal lives…The risk is low. We need to go on with our normal lives” (Woodward 2020, p. 255). Yet internally Redfield and Fauci were reportedly alarmed by the virus’s spread and had informed President Trump who was downplaying the virus.
Science Will Not Save Us
Yet, despite the rapid mobilization of federal funding and the scientific resources of the twenty-first century, COVID-19 quickly became highly politicized, particularly around masks, vaccines, and other preventative public health measures. By March 28, 2020, the U.S. had more reported COVID-19 cases than any other country and over 2,000 deaths (Woodward 2020). After the initial fifteen days of “shutdowns” of schools, sports events, and mass gatherings, Anthony Fauci and Deborah Birx urged an additional thirty-day shutdown, which was announced by Trump on March 29. They warned that, without mitigation measures, deaths could exceed 100,000; ultimately, U.S. deaths surpassed one million.
The executive branch of the U.S. federal government, however, did not take advantage of its platform and rather embraced public denial. At the end of March, Trump told the country to “Stay calm. It will go away” (Woodward 2020, p 295). Test kits and other medical equipment were in short supply, making it difficult for scientists to trace spread. The goal of these poorly enforced ‘shutdowns’ was to “flatten the curve” so as not to overwhelm the hospital system, rather than reducing the number of total infections. Privately, Redfield told others that 15 days would not be enough time, and stated that
We’re in a two-year, three-year race. This virus will stop when it basically infects more than 70 percent of the world, or 80 percent of the world…Or the world develops a biological countermeasure that stops it (Woodward 2020, pp. 282-283).
By then, it was clear that the Trump administration was inadequately prepared for a pandemic. They had disregarded a “pandemic playbook” left behind by the previous administration and had opted to disseminate medically incorrect rhetoric. This made it more difficult to coordinate a national response to contain the virus. This also resulted in a lack of essential testing supplies and medical equipment, notably ventilators The response was so inadequate that models in early April were projecting 1.5 to 2.2 million deaths nationwide without mitigation measures (Woodward 2020).
Furthermore, a deep political divide resulted through misinformation about the severity of the illness and the need for preventative barriers like masks. By April 3 (with the death toll rapidly approaching 20,000 Americans), the CDC issued guidance recommending that Americans wear masks, which Trump countered in a briefing that “This is voluntary” (Woodward 2020, p 297). Meanwhile, Fauci, Birx and Redfield were working on a three-phase plan for governors to re-open schools, business, and public spaces in their state if they showed a 14-day downward trajectory in coronavirus cases.
Fauci, however, warned that governors would try to reopen too quickly and that cases would rebound. This is exactly what happened, as governors were eager to jumpstart their economies and by April 30, many states had reopened or announced plans to reopen despite not meeting re-opening criteria. By May 6, some 70,000 people had died of coronavirus in the U.S. (Woodward 2020, p. 323). Redfield continued to believe that the vaccine would be the “magic bullet” which would stop the virus but would take 2-3 years to develop.
Capitalism
The COVID-19 pandemic has made both the capital held by the world’s wealthiest and the number of people in the viral underclass expand dramatically. Globally, the World Bank has estimated that as many as one hundred and fifty million people were pushed into extreme poverty by the COVID-19 pandemic by 2021. At the same time, a report by the Swiss bank UBS found, the world’s billionaires’ wealth soared to upward of ten trillion The Viral Underclass pp. 7-8.
The “essential” workforce (disproportionately composed of women, people of color, and immigrants) had to work under structural inequities that became even more lethal during the crisis. Indeed, 20.5 million jobs had been lost in April, and the unemployment rate was at 14.7% (Woodward 2020).
As a result, COVID-19 has disproportionally affected communities of color—in addition to either losing jobs or working at jobs that provided inadequate support for the virus—systemic inequalities like overcrowded housing conditions, and lack of access to medical care exacerbated death rates in communities of color. Similarly, HIV/AIDS has disproportionately affected communities of color, a disparity often linked to systemic inequities such as more limited access to healthcare, unequal access to education about HIV prevention, and reduced availability of preventative measures such as PrEP (pre-exposure prophylaxis) and other barrier contraceptives.
Air travel was a major route of COVID-19 transmission. Travel from China to the United States increased fourfold during the early stages of the outbreak (Woodward 2020, pp. 233–234). As Robert Redfield later noted, China’s failure to restrict outbound international flights allowed Europe and the United States to “silently” fill with COVID-19 infections.
At the same time, air travel and tourism were deeply tied to economic interests. Airlines globally lost an estimated $372 billion in passenger revenue in 2020, representing roughly a 60% decline in passenger traffic. Industry organizations such as the International Air Transport Association opposed policies such as mandating empty middle seats for social distancing, arguing that most flights require approximately 77% occupancy to remain financially viable. As in many other service sectors, workers connected to the airline and tourism industries faced heightened exposure risks while often lacking adequate protections. Consequently, communities with high levels of air travel and large populations of service and tipped workers were among the most vulnerable to the spread of the disease.
Airline industry groups also successfully lobbied the Biden/Harris administration to ease or eliminate several air travel restrictions and public health measures. In an era of rapid global travel and disease transmission, limiting transmission through air travel is common sense; however, these policies were heavily shaped by economic pressures and the financial interests tied to the airline and tourism industries.
Finally, inconsistent enforcement of mass vaccination policies reduced the long-term effectiveness of the initial COVID-19 vaccination campaign as new variants continued to emerge in subsequent years. Vaccine hesitancy, legal challenges to mandates, and political polarization weakened efforts to achieve comprehensive, high-coverage vaccination, particularly in the United States.
The consequences disproportionately affected low-income and uninsured populations. After federal subsidies for COVID-19 vaccines were reduced and, in August 2024, the Centers for Disease Control and Prevention ended a major adult vaccine safety-net program, many uninsured individuals faced substantial out-of-pocket costs for updated vaccines. In contrast, those with private insurance, Medicare, or Medicaid generally continued to receive vaccinations for free. However, these disparities were intensified by the “Medicaid unwinding” process, during which millions of Americans lost health coverage in 2024 and 2025 as states ended pandemic-era enrollment protections. As a result, the uninsured population grew at the same time that public vaccine subsidies and protections were being scaled back.
The viral underclass was larger than ever.
I started gathering data for these articles in 2020 and was tracking real-time COVID data and news articles. I have many more articles focusing on STEM academia’s hypocritical response to COVID-19.
Welcome, and thanks for signing up! Please consider following me on my social media platforms:
References
Gauchat, Gordon. 2012. “Politicization of Science in the Public Sphere: A Study of Public Trust in the United States, 1974 to 2010.” American Sociological Review 77(2): 167–87.
Rangel-Medina, Evelyn Marcelina. 2025. 66 Boston College Law Review The Disposable “Essential” Workers of COVID-19.
Thrasher, S. W. (2022). The Viral Underclass: The human toll when inequality and disease collide. Celadon Books.
Woodward, Bob. 2020. Rage. New York City: Simon & Schuster.